What wRVUs Actually Measure — and Why They Anchor Physician Compensation

After a full clinic day, you close your charts and move on. Weeks later, a compensation statement arrives with a wRVU total that doesn’t seem to match the volume or complexity of the work you did. Reconciling those numbers can feel nearly impossible.
This frustration is common among physicians navigating productivity-based pay for the first time. While wRVUs are designed to standardize clinical effort across different specialties and procedures, most physicians first see the term in an employment contract, without any context for what it captures, how it’s calculated, or what can cause the number to come in lower than expected.
The gap between the work you perform and what gets credited isn’t necessarily an error. It’s often the result of routine workflows, such as coding lag, fee schedule changes, or contract mechanics that nobody walked you through.
Once you understand how those mechanics operate, the numbers become far easier to track. This article traces the full path: what a wRVU actually measures, why health systems anchor compensation to it, how production moves through tiered thresholds and normalization adjustments, and how to verify your own statements.
What a wRVU actually measures
A Work Relative Value Unit (wRVU) is a standardized unit of physician work that quantifies the time, technical skill, mental effort, clinical judgment, and stress required to perform a specific clinical service.
The Centers for Medicare & Medicaid Services (CMS) sets these values nationally. For any given clinical activity, a wRVU earned in a rural outpatient clinic and one earned at an academic medical center represent the same unit of physician work. The practice setting does not change the baseline value of the activity.
The three components of an RVU, and why only one drives physician pay
A total RVU is the sum of three distinct components:
| Component | What it includes | What it measures | Who it serves |
| Work RVU (wRVU) | Physician time, skill, judgment, effort, and stress | The physician’s personal clinical contribution | The physician-employer relationship |
| Practice expense RVU (PE RVU) | Clinic space, staff, supplies, and equipment | The overhead cost of delivering the service | The practice/payer relationship |
| Malpractice RVU (MP RVU) | Professional liability insurance costs | The liability risk associated with the service | The practice/payer relationship |
Physicians do not control practice expenses or malpractice costs: staffing models, facilities, and equipment are determined at the health system level. Isolating the work component ensures that compensation reflects what the physician personally contributed, rather than the cost environment in which they operate.
When an activity (billing, productivity) report displays a total RVU figure, it includes all three components. When a compensation statement shows wRVUs, it includes only the first. When these two values get confused, reconciling production against pay becomes even more frustrating.
Why completed work may not appear in your production report yet
Completed clinical work and reported production often move on different timelines. wRVUs are credited based on when activity is processed and logged in the system, which means there is inherently a gap between the service date and the posting date.
Understanding this lag is key to tracking your numbers. An encounter completed near the end of a month might not post until the following reporting cycle, creating a temporary gap between the care you delivered and the credit currently reflected on your statement.
This is why near-real-time visibility into production data matters. Rather than waiting weeks for a static end-of-period report, having continuous access to your posted wRVUs makes it easier to understand what has been credited so far, track activity as it posts, and monitor how your production is accumulating over time.
The visibility you deserve
The Simpliphy Mobile App allows physicians to track earnings and production as activity moves through the compensation workflow.
What wRVU values look like in practice
wRVU values vary significantly by service complexity and procedure type. Consider these examples (based on 2026 values):
- Established patient office visit, moderate complexity (99214): 1.92 wRVUs
- Routine preventive visit, adult (99396): 1.90 wRVUs
- Colonoscopy with biopsy (45380): 3.47 wRVUs
- Open appendectomy (44950): 10.34 wRVUs
- Total knee replacement (27447): 19.11 wRVUs
Because wRVUs scale with service intensity, production patterns look vastly different across medical and surgical specialties. A primary care physician seeing a panel of established patients generates wRVUs incrementally through routine office visits, while procedural specialties accumulate wRVUs around specific, episode-based cases. Both outcomes accurately reflect the model, driving the differences in how specialty compensation contracts and volume thresholds are structured.
Why wRVUs became the compensation standard
The wRVU was adopted because healthcare needed a standardized, objective metric to measure physician clinical labor independent of practice overhead, facility fees, or collections, and one that could withstand federal regulatory scrutiny.
Physician compensation models are constrained by federal regulations, specifically Stark Law and the Anti-Kickback Statute, which require that physician compensation reflect Fair Market Value (FMV) and be commercially reasonable. A simplified way to demonstrate FMV is to compare a physician’s wRVU production percentile against their total compensation percentile using national benchmark surveys. When those two percentiles align, the health system has a defensible basis for what it is paying.
The wRVU is the unit that makes that comparison possible. It provides an objective, market-based measure of clinical labor that holds across specialties, settings, and practice structures, making it the ideal anchor for productivity-based compensation.
How compensation models use wRVUs
Once you understand what a wRVU measures, you can look at how those units translate into a paycheck. The compensation logic used to make that calculation varies considerably from one employer to the next.
Productivity mechanics
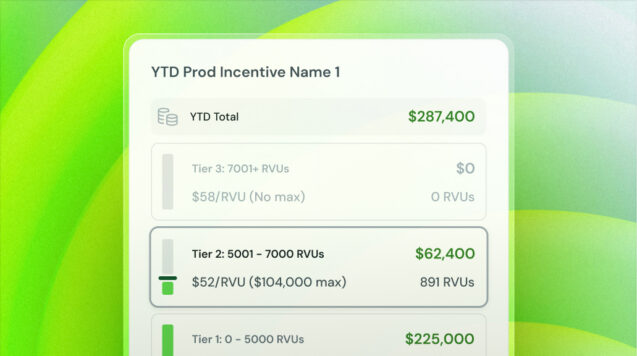
Many production-based contracts establish a per-wRVU rate, often structured in tiers that reward higher output. Here’s a simplified example:
- Tier 1: 0–5,000 wRVUs at $55/wRVU
- Tier 2: 5,001–7,500 wRVUs at $60/wRVU
- Tier 3: 7,501+ wRVUs at $65/wRVU
In this structure, the rate applied to each wRVU depends on which tier the physician is in when that unit is earned. A physician finishing the year at 7,800 wRVUs receives $65 per unit only on the 300 exceeding the Tier 3 threshold.
Many contracts also include a base salary draw, which functions as an advance against expected production. If a physician doesn’t generate enough wRVUs to cover that draw by year-end, they may not earn a bonus. In some contracts, they may face reconciliation, where the shortfall is carried over or offset against future earnings. The specific terms vary, and they matter more than the nominal per-wRVU rate when evaluating what a contract is actually worth.
Normalization adjustments
Physicians who hold administrative, teaching, or research roles alongside patient care are typically assigned a reduced clinical FTE. Production targets must be normalized accordingly.
A physician working 0.6 clinical FTE should not be held to the same production threshold as a full-time clinician. Failing to adjust targets proportionally creates a benchmark that is structurally unachievable within the allocated clinical hours.
When evaluating an employment contract or annual target, the clinical FTE allocation and its corresponding wRVU threshold should be explicitly linked. If the threshold does not scale down with clinical FTE, that discrepancy should be resolved before signing.
Verifying your compensation statement
Reconciling a compensation statement against your actual clinical workload comes down to verifying three core mechanics:
- Production capture: Confirm that all completed encounters from your clinical log have posted to your current statement. If a recent clinic day seems missing, check whether those encounters closed before or after the monthly billing cutoff date.
- Contract logic application: Check that the correct per-wRVU rate or tier was applied to your cumulative output, and verify that your production target properly reflects your assigned clinical FTE.
- Draw and reconciliation math: Ensure any base salary draw, prior-period adjustments, or bonus withholdings align with your contract’s exact reconciliation schedule.
When clinical logs, contract terms, and payroll summaries live in separate health system platforms, manually auditing these variables each month requires cross-referencing multiple reports. Platforms like the Simpliphy Mobile App simplify this by bringing your posted production, contract logic, and payout calculations into a single view, making it straightforward to see how your clinical work translated into your paycheck.
Common misconceptions about wRVUs
Why patient satisfaction and undocumented efforts don't generate wRVUs
Some care coordination activities, such as patient callbacks, inbox management, prior authorizations, and multidisciplinary coordination, are not coded services under standard workflows. Because the wRVU model measures documented clinical volume, the gap between credited output and total physician effort can be substantial.
This gap is a primary source of frustration for physicians who feel their compensation does not reflect the full scope of their daily effort. The wRVU model is not designed to capture total workload; it captures coded clinical volume.
Why dollar-per-wRVU rates vary across specialties
A higher dollar-per-wRVU conversion rate does not automatically guarantee higher net compensation. Specialty conversion rates differ significantly because baseline wRVU potential varies by clinical specialty. A proceduralist generating 9,000 wRVUs annually and a primary care physician generating 5,500 wRVUs require different per-unit rates to align with Fair Market Value (FMV) benchmarks and total target compensation.
Per-wRVU rates are also heavily influenced by regional market demand and geographic cost-of-living adjustments. Volume and rate interact, and evaluating either number in isolation gives an incomplete picture of a contract’s actual financial value.
Disentangling wRVU volume from your final paycheck
A raw wRVU total measures clinical activity, not a direct dollar figure. The path from wRVU production to a paycheck runs entirely on contract structure: base salary draws, production thresholds, tiered conversion rates, and FTE allocations all affect the final number. Physicians expecting a simple calculation of total wRVUs multiplied by a flat rate often find their final pay stub does not match their expectations because the contract mechanics intervene between production and payout.
When your production, compensation logic, and earnings are separated across different reports or delayed statements, verifying how pay was calculated becomes difficult. Having continuous visibility into how monthly wRVU output translates to pay through specific contract mechanics allows physicians to reconcile their compensation in real time.
Where wRVU-based models create tension
The wRVU model captures clinical volume, but it does not reflect the quality of outcomes, the complexity of a patient’s situation, or time spent on undocumented care coordination. While most modern compensation structures layer additional incentives over production to address this gap, physicians must understand the limits of the wRVU and how other metrics impact overall pay.
What wRVUs don't capture about clinical performance
Several vital aspects of clinical practice generate few or no wRVUs under standard workflows:
- Care quality and patient outcomes: A physician who achieves better outcomes through more thorough visits generates fewer wRVUs than one who moves faster through the same panel.
- Preventive care effectiveness: Keeping patients out of the hospital doesn’t produce a coded encounter.
- Care coordination: While specific Medicare programs offer CPT codes for formal coordination, informal record reviews, specialist communication, and care transition management are not credited under standard wRVU models.
- Teaching and supervision: Time spent with residents or students reduces clinical throughput without lowering the wRVU target.
A physician who sees fewer patients to deliver highly complex, personalized care will appear less productive on a wRVU report than a peer focused purely on volume. The wRVU metric measures units of activity, not holistic care value.
Layering quality incentives and value-based metrics on top of wRVU production
Most modern employment contracts don’t rely on wRVUs alone. Quality bonuses, HEDIS performance measures, patient satisfaction scores, and value-based care incentives are commonly layered on top of the production base. The wRVU remains the anchor for the compensation structure, but it is one component of a broader model.
Because each layer operates on different data sources, timelines, and thresholds, physicians must evaluate them independently. A quality bonus tied to HEDIS measures follows a different calculation schedule than monthly wRVU production. Missing the logic on one component means you can’t verify whether the total is right, and the total is what actually hits your account.
Why primary care physicians and proceduralists experience the model differently
The wRVU model impacts medical and surgical specialties in fundamentally different ways.
Proceduralists generate high wRVU totals through discrete, high-intensity interventions. A surgeon performing several complex cases each week accumulates wRVUs at a rate a primary care physician seeing a full panel of established patients cannot match. Not because the primary care physician is less productive, but because the wRVU values assigned to cognitive, evaluation-and-management (E/M) care are structurally lower than those assigned to procedural services.
Because purely productivity-based models inherently favor procedural throughput, health systems frequently adapt primary care compensation. These adaptations often incorporate panel size adjustments, value-based quality pools, or capitated care bonuses to better reflect non-procedural contributions. However, the degree to which an employer balances these metrics varies widely across organizations.
Take control of your compensation literacy
Understanding wRVUs is essential to protecting your pay and ensuring your contract works as intended. When you view your monthly statement as the final output of a multi-step administrative pipeline, you become an active participant in your compensation, catching discrepancies early and forecasting earnings to make more informed decisions about your practice.
To stay on top of your numbers, make a habit of closing charts promptly, verifying that your FTE normalization reflects any non-clinical responsibilities, and monitoring production as care is delivered rather than months down the road. The earlier you catch a discrepancy, the easier it is to trace and correct.
The challenge is that most physicians lack a clean way to monitor their wRVUs in real time. Without the context needed to independently reconcile their numbers, physicians are often left disputing pay statements after the fact.
This is the visibility gap the Simpliphy Mobile App was built to bridge. By unifying wRVU tracking, compensation, and earnings forecasting into a single intuitive experience, Simpliphy gives physicians complete clarity over their production as it happens, not weeks after the statement arrives.

The Simpliphy Team combines experience in physician compensation, healthcare finance, operations, and technology to help health systems navigate one of their most complex administrative functions. Through practical insights and firsthand experience, our team shares perspectives that help organizations simplify compensation, improve transparency, and make more informed decisions.

Danny McNight is Director of Marketing at Simpliphy, leading the development of campaigns and brand experiences that make complex ideas clear and compelling. With a background in digital creative direction, he helps shape how Simpliphy communicates its value across channels and audiences.